THYROID GLAND
THYROID GLAND. MUST KNOW. How to examine the neck and diagnose thyroid enlargement from other neck lumps. Clinical presentation of hypo and hyper Meaning and interpretaion of thyroid function tests. How to investigate and manage a patient with STN


THYROID GLAND
E N D
Presentation Transcript
MUST KNOW • How to examine the neck and diagnose thyroid enlargement from other neck lumps. • Clinical presentation of hypo and hyper • Meaning and interpretaion of thyroid function tests. • How to investigate and manage a patient with STN • Clinical features ,dx and management of thyroid neoplasms
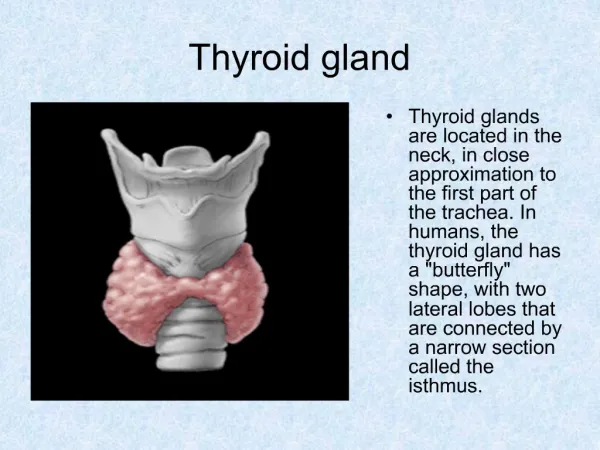
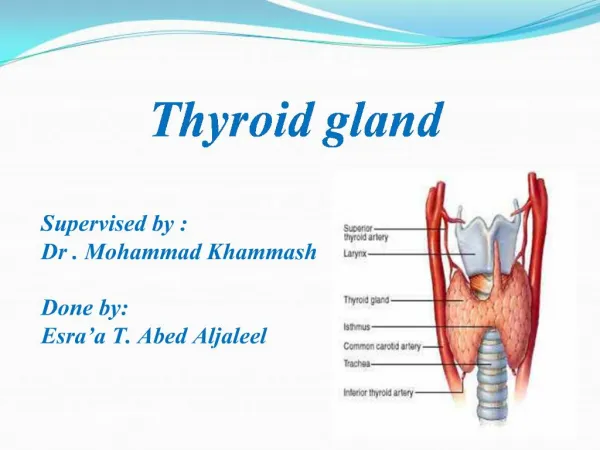
ANATOMY AND PHYSIOLOGY • WHY DOES THE YHROID MOVE ON SWALLOWING.
MIDLINE SWELLINGS • Thyroid enlargement • Thyroglossal cyst • Dermoid cyst
HYPOTHYROIDISM • F:M 10:1 • Due to commonly hashimotos[TPO AND ANTI THYROGLOBULIN IS RAISED] • Symptoms and signs • Exam • Lymphoma can develop on a back ground of autoimmune disease • TSH,T4 ,T3 • TX Thyroxine
hyperthyroidism • Causes include • Grave’s • Toxic multinodular goiter • Solitary toxic adenoma • Tx with thyroid uptake drugs • radioactive iodine • surgery
MNG • Majority are non toxic • Some can become toxic ( plummers disease) • May extend retrosternally if large causing trachael deviation, compression and strider • O/E multinodular if there is dominant nodule then this should be investigated as the risk of malignancy in this nodule is about 10%.
TSH : Low if toxic • FNA • US • X-ray of thoracic inlet • Tx – Total for non-toxic if there is retrosternal ext., trachael comp or cosmotically unacceptable • If toxic - tx first the either total or radioactive iodine
SOLITARY THYROID NODULE • 5% Of female population. But only 5% are malignant. • Causes 1- thyroid cyst 2- degenerative thyroid nodule 3- benign follicular adenoma 4- differentiated thyroid ca
History • Feature suggestive of malignancy 1- previous irradiation (as a child) 2- hoarsness 3- family Hx (papillary)
Investigation • Exclude solitary toxic adenoma (where TSH is suppressed) + malignancy therefore TSH and FNA most important • If suspicious on FNA then for surgery as 30% are malignant • Ultrasound to distinguish solid from cystic or dominant nodule within MNG (50% STN)
Isotope scan Increase uptake = hot Decreased uptake = cold • Treatment
Thyroid tumours Benign thyroid tumours • Most are follicular adenomas • Papillary adenomas are rare • All papillary tumours should be considered malignant
Follicular adenoma • Of all follicular lesions-80% benign and 20% malignant • They are smooth and discrete lesions with glandular or acinar pattern • They are incapsulated usually 2-4 cm in diameter • Adenomas can not be differentiated from carcinoma on FNA cytology • Requires histological assessment of capsular invasion
Malingnat thyroid tumours • Differentiated thyroid cancer accounts for 80% of thyroid neoplasms • Female : Male ratio is 4:1 • Usually presents as solitary thyroid nodule in young/middle age adult • Nodule more likely to be malignant in man or child • Papillary and follicular tumours are biologically very different
Comparison of papillary and follicular tumours • Papillary tumours Follicular tumours • Multifocal Solitary • Unencpasulated Encapsulated • Lymphatic spread Haematogenous spread • Metastasize to Metastasize to lung. regional bone and brain
Papillary and mixed tumours • Accounts fro 70% Of Ca. thyroid. • 20-40 yrs • 50% tumours are less than 2cm diameter at presentation • Tumours less than 1cm diameter regarded as minimal or micropapillary lesoins • Psammoma bodies and “orphan Annie” nuclei are characteristic histologicalfeatures
30%-50% are multicentric with simultaneous tumour in contralateral lobe • Early spread occurs to regional lymph nodes • Thyroid lobectomy adequate for minimal lesions • Total thyroidectomy is otherwise surgery of choice
Many tumours are TSH dependent • TSH suppression with post-operative thyroxine appropriate • Thyroxine reduces recurrence and improves survival • 80% nodes have microscopic involvement • Role of prophylactic lymph node dissection at time of initial surgery unclear
Lymph node dissection does not improve survival • Alternative is to sample the lymph nodes • If negative-no further surgery • If positive-modified neck dissection • Prognosis excellent (90% 20 yrs)
Follicular tumours • 40 – 50 yrs • Can not differentiate follicular adenoma and carcinoma on FNA cytology • Treatment of all follicular neoplasms is thyriod lobectomy with frozen section • If frozen section confirms carcinoma- total thyriodectomy • If frozen section confirms adenoma-No further surgery required • Total thyroidectomy allows detection of metastased using 123/Scanning during follow up • All patients require suppressive thyroxine therapy
Follow up of thyroid carcinoma • Annual isotope scanning to detect asymptomatic recurrence • Treatment of such recurrence can still be curative • Serum thyroglobulin-increasing levels often first sign of recurrence
Anaplastic carcinoma • Accounts for less than 5%thyroid malignancies • Occurs in elderly and is usually an aggressive tumour • Local infilteration causes dysponea and dysphagia • Thyriodectomy seldom feasible • incision biopsy should be avoided as it often causes uncontrollable local spread • Radiotherapy and chemotherapy important modes of treatment • Death usually occurs within 6 months
Thyroid lymphoma • Accounts for 2% of thyroid malignancies • Often arises with Hashimotos thyroiditis or non-Hodgkins B-cell lymphoma • Presents as a goitre in association with generalized lymphoma • Diagnosis can often be made by FNA cytology • Radiotherapy is treatment of choice • Prognosis is good – often more than 85% 5 yr survival
Medullary carcinoma • 8% • Para-follicular C-cells • 20% are familial • Can occur as part of MEN 2 • 80% of cases are sporadic • Sporadic cases usually unilateral • 50% have lymph nodes at presentation • Familial cases often multifocal and bilateral • Tumours mets to nodes and via blood to bone, liver and lung • They produce calcitonin, • Total thyroidectomy is treatment of choice • Calcitonin can be used in follow up for the presence of metastatic disease