Understanding Age-Related Macular Degeneration: Advances and Management Strategies
Age-related macular degeneration (AMD) is a leading cause of blindness in adults over 55. This degenerative disease affects the macula, leading to vision impairment. Early AMD shows minimal symptoms, while late AMD can result in severe vision loss due to neovascularization or atrophy. The Age-Related Eye Disease Study (AREDS) showed that specific nutrients can reduce progression. Recent advancements include anti-VEGF therapies, such as Lucentis and Avastin, which target the vascular endothelial growth factor, offering hope for managing this incurable condition.


Understanding Age-Related Macular Degeneration: Advances and Management Strategies
E N D
Presentation Transcript
Kevin Colleaux, MD, FRCSC Associate Clinical Professor University of Saskatchewan ARMD Update 2007
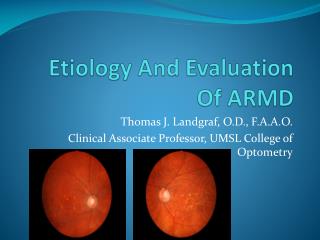
Age-related Macular Degeneration • Incurable, degenerative disease of the macula • Leading cause of blindness in adults >55 years Normal retina Early AMD Late AMD retina Neovascularization Atrophy
Impact Of Age-related Macular Degeneration 0.69 Moderate stroke (requiring help) 0.68 Moderate AMD: 20/50 to 20/100 Ulcerative colitis requiring surgery 0.58 Permanent renal dialysis 0.56 0.47 Severe AMD: 20/200 or worse Severe stroke (bedridden) 0.34 0.0 0.1 0.2 0.3 0.4 0.5 0.7 0.8 0.9 1.0 0.6 Utility score (Patient-reported) Brown GC et al. Trans Am Ophthalmol Soc 2005;103:173–84.
Age & Age-related Macular Degeneration Klein R et al. Ophthalmology 1992;99:933-943; Beaver Dam 1988
Reducing The Risk Of Developing Age-related Macular Degeneration
Uncontrollable Risk Factors • Age • Family history • Gender - female • Race • Iris color
Controllable Risk Factors • Diet • Smoking • Ultraviolet exposure • Excessive weight/obesity • Hypertension
Age Related Eye Disease Study (AREDS) • Demonstrated about 25% reduction in AMD progression with supplements: • Vit E 400 IU • Vit C 500 mg • Beta Carotene 25000 IU • Zinc 80 mg • (copper 2 mg)
Carotenoids • A subclass of xanthophylls • Yellow, oxygen-containing pigments found in plants • Dietary sources: • Spinach, collard greens, broccoli, carrots, corn, citrus fruit • Two major eye nutrients: • Lutein • Zeaxanthin
Managing Exudative AMD in 2007 • A brief history…. • Pre – 2000 • thermal laser • Vision benefit only for extrafoveal discreet lesions • 50% recurrence rate • Most cases untreatable • Treated subfoveal disease universally < 20/200 • 2000 – 2005 • PDT era • 2005 – present • Anti VEGF era
Visudyne Photodynamic Therapy (PDT) • Intravenous infusion of a photosensitive agent (verteporphin) • Laser photoactivation of drug in subretinal tissue • induces thrombosis of neovascular tissue
PDT • Slowed rate of vision loss • Modified treatment parameters and combination with kenalog reduced retreatment and possibly improves outcomes
The Anti VEGF Era • VEGF – Vascular endothelial growth factor • A potent mediator of neovascular growth • Dramatically increases vascular permeability • ‘vascular permeability factor’ • Key factor in exudative ARMD, retinal vascular disease (diabetic retinopathy), and iris neovascularization • Important in maintenance of systemic vascularity and reperfusion, wound healing
Pan VEGF vs Selective VEGF blockade • 5 major isoforms of VEGF • VEGF 165 felt to be the key isoform in ocular neovascular disease • Pegaptamib sodium (macugen) selectively inhibits VEGF 165 • Theoretically should effectively treat ocular disease with lower systemic side effects • Lucentis (ranabizumab) and Avastin (bevacizumab) block all isoforms • ‘Pan VEGF blockade’
MacugenEOP1003, 1004 Combined analysis Weeks after study enrolment Mean change in VA from baseline (number of letters) *Data points estimated from reference Gragoudas ES, Adamis AP, Cunningham ET, et al. N Engl J Med. 2004; 351: 2805–16
Macugen PDT Macugen vs PDT
Vision improvement as the new standard of care in neovascular AMD
Ranibizumab (Lucentis*) (E. coli vector to mass produce) Ranibizumab: Developed Specifically For Ocular Use (AMD) 0 Anti-VEGF-AMurine MAb rhu Fab v1 Affinitymaturation (140x) Humanization Ferrara et al, RETINA 2006; vol 26(8): 859 Data on file (Ferrara)
Lucentis (ranibizumab) vs Avastin (bevacizumab) • Identical mode of action • Efficacy should be similar • Avastin • Off – label use • Hundreds of presentations and publications over past 4 years showing efficacy and safety • Case series and reports, NOT prospective randomized trials • Comparative head to head study currently enrolling at NIH. • Full antibody • Longer half life – increased systemic effect ? • Possibly pro-inflammatory • Lucentis • The gold standard, best data proving efficacy
MARINA treatment schema Month 12 0 1 2 3 4 5 6 7 8 9 10 11 23 24 Ranibizumab0.5 mg Ranibizumab0.3 mg Sham Verteporfin at investigator discretion if: • Conversion to predominantly classic CNV, or • Loss of ≥20 letters on 2 consecutive visits and small (≤4 DA), minimally classicor occult with no classic lesions, with presumed recent disease progression Primaryendpoint prior to Rx Finalvisit Rosenfeld et al, N Engl J Med 2006; 355: 1419
Secondary endpoint:Patients gaining ≥15 letters from baseline Patients gaining ≥15 letters from baseline (%) 100 *** *** *** 34 33 *** 26 25 5 4 0 n=238 238 240 n=189 209 215 Month 12 Month 24 Sham(n=238) Ranibizumab 0.3 mg(n=238) Ranibizumab 0.5 mg(n=240) ***p<0.001 vs sham Rosenfeld et al, N Engl J Med 2006; 355: 1419
Ranibizumab 0.3 mg (n=238) ETDRS letters 10 +7.2 +6.6 +5.4 5 +6.5 21.5 letter difference*** 0 2 4 6 8 10 12 14 16 18 20 22 24 -5 20.3 letter difference*** -10.4 -10 -15 -14.9 Month Secondary endpoint:Mean change in VA over time Sham (n=238) Ranibizumab 0.5 mg (n=240) ***p<0.001 vs sham Rosenfeld et al, N Engl J Med 2006; 355: 1419
Secondary endpoint:Patients with 20 / 200 or worse Patients (%) 100 48 43 *** *** *** *** 15 15 15 13 13 12 12 0 Baseline Month 12 Month 24 Sham(n=238) Ranibizumab 0.3 mg(n=238) Ranibizumab 0.5 mg(n=240) ***p<0.001 vs sham Rosenfeld et al, N Engl J Med 2006; 355: 1419
MARINA 24 monthsSecondary endpoint:Patients with 20 / 40 or better Patients (%) 100 *** *** *** 42 40 *** 39 35 15 15 11 11 6 0 Baseline Month 12 Month 24 Sham(n=238) Ranibizumab 0.3 mg(n=238) Ranibizumab 0.5 mg(n=240) ***p<0.001 vs sham Rosenfeld et al, N Engl J Med 2006; 355: 1419
Summary: MARINA year 2 results • Ranibizumab 0.5 mg patients had a +6.6 letter improvement in visual acuity • 33% of ranibizumab 0.5 mg patients improved ≥15 letters vs 4% of sham patients • 90% of ranibizumab patients lost fewer than 15 letters vs 53% in sham arm Rosenfeld et al, N Engl J Med 2006; 355: 1419
ANCHOR treatment schema Ranibizumab 0.3 mg Ranibizumab 0.5 mg Sham injection Verteporfin Sham PDT 12 Month 0 1 2 3 4 5 6 7 23 24 8 9 10 11 Ranibizumab 0.3 mg Ranibizumab 0.5 mg Verteporfin Sham Primary endpoint Final visit Brown et al, N Engl J Med 2006; 355: 1432
Primary endpoint:Patients losing <15 letters from baseline Patients (%) *** *** 96.4 94.3 100 64.3 0 Month 12 Verteporfin (n=143) Ranibizumab 0.3 mg (n=140) Ranibizumab 0.5 mg (n=139) Brown et al, N Engl J Med 2006; 355: 1432 ***p<0.001 vs verteporfin
Secondary endpoint:Patients gaining ≥15 letters from baseline Patients (%) 100 *** *** 40 36 6 0 Month 12 Verteporfin (n=143) Ranibizumab 0.3 mg (n=140) Ranibizumab 0.5 mg (n=139) Brown et al, N Engl J Med 2006; 355: 1432 ***p<0.001 vs verteporfin
Secondary endpoint:Mean change in VA over time Verteporfin (n=143) Ranibizumab 0.3 mg (n=140) Ranibizumab 0.5 mg (n=139) ETDRS letters 15 +11.3 10 +8.5 20.8 letter difference*** 5 0 18 letter difference*** 2 4 6 8 10 12 -5 -9.5 -10 -15 -20 Month ***p<0.001 vs verteporfin Brown et al, N Engl J Med 2006; 355: 1432
Secondary endpoint:Patients with VA 20 / 200 or worse Patients (%) 100 60 32 *** 25 *** 23 22 16 0 Baseline Month 12 Verteporfin (n=143) Ranibizumab 0.3 mg (n=140) Ranibizumab 0.5 mg (n=140) ***p<0.001 vs verteporfin Brown et al, N Engl J Med 2006; 355: 1432
Exploratory endpoint:Maintaining baseline VA or gaining ≥0 letters Patients (%) 100 *** *** 77 74 30 0 Month 12 Verteporfin (n=143) Ranibizumab 0.3 mg (n=140) Ranibizumab 0.5 mg (n=140) Data on file (ANCHOR 12 months) ***p<0.001 vs verteporfin
ANCHOR 12 monthsSecondary endpoint:Patients with VA 20 / 40 or better Patients (%) 100 *** *** 39 31 4 3 1 0 0 Baseline Month 12 Verteporfin (n=143) Ranibizumab 0.3 mg (n=140) Ranibizumab 0.5 mg (n=140) ***p<0.001 vs verteporfin Brown et al, N Engl J Med 2006; 355: 1432
Summary: ANCHOR year 1 results • Ranibizumab 0.5 mg patients had a +11.3 letter improvement in visual acuity • 40% of ranibizumab 0.5 mg patients improved ≥15 letters vs 6% of verteporfin patients • 96.4% of ranibizumab patients lost fewer than 15 letters vs 64.3% in sham arm Brown et al, N Engl J Med 2006; 355: 1432
PIER treatment schema 0 0 1 2 3 4 5 6 7 8 9 10 11 12 23 24 Month Ranibizumab 0.5 mg Sham Primaryendpoint Finalvisit PIER 12 months
10 5 0 -5 -10 -15 PIER:Mean change in VA over 12 months 0 ETDRS letters -0.2 1 2 3 4 5 6 7 8 9 10 11 12 16.1 letterdifference*** -16.3 Month Sham (n=63) Ranibizumab 0.5 mg (n=61) PIER 12 months ***p<0.001 vs sham
Serious ocular safety conclusions 0 • Ocular serious adverse events were not common in ranibizumab-treated patients • <1.5% for each adverse event • Per injection rate of endophthalmitis was <0.1% Rosenfeld et al, N Engl J Med 2006; 355(14): 1419 Brown et al, N Engl J Med 2006; 355(14); 1432
Potential side-effects ofsystemic VEGF inhibition • Arteriothromboembolic events (ATEs) • Assessed using APTC√ criteria • broader scope of event types • Hypertension • Non-ocular hemorrhage • Proteinuria • Other (GI perforation, Impaired wound healing) √Antiplatelet Trialists’ Collaboration, BMJ 1994; 308(6921): 81–106 van Wijngaarden P, JAMA. 2005;293(12):1509-13
Summary of systemic safety • No statistically significant differences in the distribution of ATEs between ranibizumab and control or between the two ranibizumab doses • No higher incidence compared with general AMD population • Patients with cardiovascular history were not excluded from enrollment into ranibizumab studies MARINA and ANCHOR studies
Lucentis (ranibizumab) vs Avastin (bevacizumab) • Identical mode of action • Efficacy and toxicities should be similar • Avastin • Off – label use • Hundreds of presentations and publications over past 4 years showing efficacy and safety • Case series and reports, NOT prospective randomized trials • Comparative head to head study currently enrolling at NIH. • Full antibody • Longer half life – increased systemic effect ? • Possibly pro-inflammatory • Lucentis • The gold standard, best data proving efficacy
Combination therapy • ½ fluence PDT • Plus Avastin / Lucentis • DENALI trial • Plus avastin and dexamethasone • Triple therapy, (Augustin)
Vision improvement as the new standard of care in neovascular AMD